
Early H1N1 Wave Pushes US Flu Hospital Rate to Highest Mid-October Level Since 2010-11, CDC Data Show

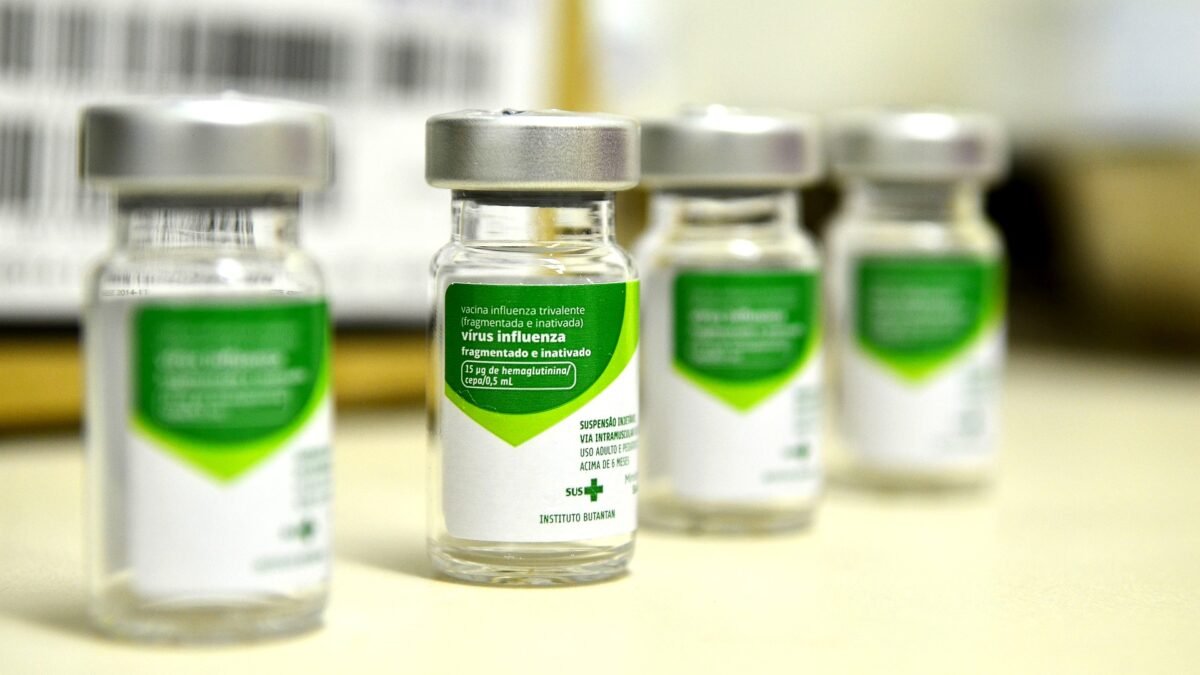
Flu season in the United States has started earlier than usual, and the first clear hospital signal of the 2026-27 season is now in the official record. According to the Centers for Disease Control and Prevention (CDC), the estimated flu hospitalisation rate for the week ending 17 October 2026 was the highest for that week of the season since 2010-11, even though overall flu activity in the country remained low.
The finding comes from the CDC’s Weekly US Influenza Surveillance Report for Week 41, published on 23 October 2026. The CDC said seasonal influenza activity was increasing in many parts of the country but remained low nationally. It also said that multiple indicators — the share of specimens testing positive for influenza, outpatient visits for influenza-like illness, emergency department visits with an influenza diagnosis, and laboratory-confirmed flu hospitalisations — had been rising since late August or early September 2026.
“Early-season influenza activity is currently higher than typically observed at this time of year,” the CDC said, according to the report. The agency added a caution that belongs in every reading of the figures: every influenza season is different, some begin earlier than usual and others later, and an early start on its own does not settle how severe the season will become.
The hospitalisation headline rests on FluSurv-NET, the CDC’s population-based network for laboratory-confirmed influenza hospitalisations in selected counties in 14 states, covering approximately 10 per cent of the US population. The network reported 798 laboratory-confirmed influenza-associated hospitalisations between 4 October and 17 October 2026. The observed weekly hospitalisation rate in Week 41 was 1.1 per 100,000 population, the same as in the previous week. After accounting for reporting delays, the CDC estimated that the Week 41 rate likely ranged from 1.5 to 2.0 per 100,000.
“This is the highest weekly rate for Week 41 since the 2010-2011 season,” the CDC said, according to the report. The cumulative hospitalisation rate observed in Week 41 was 2.1 per 100,000 population. The CDC stressed that FluSurv-NET data are preliminary and that earlier counts and rates are updated as more reports arrive, so the Week 41 figures may still move.
A second hospital system told a consistent story at a larger scale. Hospitals reporting to the National Healthcare Safety Network recorded 4,811 laboratory-confirmed influenza-associated hospitalisations in Week 41, according to the CDC. The admission rate was 1.4 per 100,000 population, stable compared with Week 40 but trending upward. Regional admission rates ranged from 0.6 per 100,000 in Region 5 to 2.0 per 100,000 in Region 4, and rates increased in Regions 1, 4, 6 and 10.
Age remains the sharpest divider in the hospital data. In FluSurv-NET, the highest hospitalisation rate was among adults aged 65 and older, at 7.4 per 100,000, followed by adults aged 50 to 64 at 2.3 and children aged 0 to 4 at 1.7, according to the CDC. Adults aged 18 to 49 recorded 0.6 per 100,000 and children aged 5 to 17 recorded 0.5 per 100,000. In the national hospital admissions data, the highest rate was again among people aged 65 and older, at 4.6 per 100,000, followed by children aged 0 to 4 at 1.5 and adults aged 50 to 64 at 1.4. The two systems use different catchment areas and methods, so their rates are not interchangeable, but both point the same way: older adults are bearing the heaviest hospital burden so far, with the youngest children next in line.
The CDC also published age-adjusted rates by race and ethnicity from FluSurv-NET. The highest rate was among non-Hispanic Black people, at 3.2 per 100,000, followed by Asian and Pacific Islander people at 2.6, Hispanic people at 1.8, non-Hispanic White people at 1.7, and American Indian or Alaska Native people at 1.2. Those figures describe who has been hospitalised in the surveillance counties so far; they do not by themselves explain why, and the CDC’s report does not attribute the differences to any single cause. Differences of this kind in respiratory illness surveillance commonly reflect a mix of exposure, underlying health, access to care and vaccination, and the age structure and geography of the counties covered, and they require local data before any firmer interpretation is possible.
The laboratory picture explains why this early rise looks different from last winter. In Week 41, clinical laboratories tested 51,490 respiratory specimens, of which 2,918, or 5.7 per cent, were positive for influenza, according to the CDC. That was up from 5.0 per cent in the previous week and 3.9 per cent two weeks earlier. Influenza A accounted for 97.9 per cent of the positive clinical-laboratory specimens, and influenza B for 2.1 per cent.
Public health laboratories, which subtype a share of viruses to track which strains are circulating, reported 323 positive specimens in Week 41, of which 318 were influenza A and five were influenza B. Of the 241 influenza A viruses subtyped that week, 239, or 99.2 per cent, were influenza A(H1N1)pdm09, two, or 0.8 per cent, were A(H5), and none were A(H3N2). The H3N2 absence was a one-week result, not a season-wide one: since 4 October, public health laboratories had subtyped 16 H3N2 viruses among 798 subtyped influenza A viruses, alongside 780 H1N1 viruses. H3N2 is therefore circulating at a low level, even though it did not appear in the Week 41 subtyping sample.
Among hospitalised patients in FluSurv-NET with subtype information, 112, or 98.2 per cent, had A(H1N1)pdm09 and two, or 1.8 per cent, had A(H3N2), according to the CDC. Overall, 777 of the 798 FluSurv-NET hospitalisations, or 97.4 per cent, were associated with influenza A, 20, or 2.5 per cent, with influenza B, and one with a virus whose type was not determined.
The two A(H5) specimens in the public health laboratory count need careful handling, because specimens are not the same as human cases. The CDC explained in the same report that the public health laboratory data reflect specimens tested, can include more than one specimen per person, and include targeted testing of people exposed to avian influenza A(H5) viruses. Separately, the CDC reported one confirmed human infection with avian influenza A(H5N1) virus during Week 41. That case, reported by the Washington State Department of Health, was in a worker aged 18 or older at a commercial dairy cattle farm where highly pathogenic avian influenza A(H5N1) had been detected in cows. The person developed eye irritation and upper respiratory symptoms, and the infection was confirmed by the state public health laboratory and by additional CDC testing. It was the first influenza A(H5) case associated with a dairy worker in Washington, according to the CDC.
“To date, human-to-human transmission of avian influenza A(H5) virus (H5 bird flu) has not been identified in the United States,” the CDC said, according to the report. The H5N1 case is therefore a separate surveillance event from the seasonal H1N1 wave, not evidence that bird flu is spreading between people or driving the seasonal rise. Keeping the two apart matters, because conflating a single occupational exposure with a national seasonal trend would misstate both risks.
Outpatient and emergency department data show a season that is moving, but has not yet reached the levels associated with peak winter activity. Nationally, 2.2 per cent of patient visits reported through the CDC’s outpatient influenza-like illness network in Week 41 were due to influenza-like illness, stable compared with Week 40 and below the national baseline of 2.9 per cent, according to the CDC. All regions were below their own baselines. Visits for respiratory illness increased in children aged 0 to 4 and in people aged 5 to 24, and remained stable in older age groups.
Emergency department visits with a discharge diagnosis of influenza accounted for 0.9 per cent of visits nationally in Week 41, stable compared with the previous week, according to the CDC. The share increased among children aged 0 to 4 and 5 to 17, and remained stable among adults. At a more local level, the number of metropolitan areas at moderate influenza-like illness activity rose from eight in Week 40 to 25 in Week 41, while the number of jurisdictions at moderate activity rose from one to two. Most of the country remained at minimal activity, but the jump in moderate metropolitan areas is an early sign of local hot spots forming before the national average moves much.
Mortality surveillance, which lags behind hospital data, had not yet shown a seasonal rise. Based on data available on 22 October, 0.2 per cent of deaths in the week ending 17 October were due to influenza, stable compared with Week 40, according to the CDC. No influenza-associated paediatric deaths occurring during the 2026-27 season had been reported to the CDC.
Geography is one of the most unusual features of this season so far. Flu seasons in the United States usually build first in southern states and move north. This year the earliest rise began in the west, and scientists have not determined why, according to reporting of the CDC data by Reuters. The CDC’s previous weekly report placed the highest activity in the two federal health regions covering the West Coast, including California, Oregon, Washington, Nevada, Arizona, Hawaii, Alaska and Idaho.
Reuters reported that the 5.0 per cent test positivity recorded in the week ending 10 October was a 10-year high for that point in the year, and that West Coast positivity reached 10.7 per cent, compared with 0.5 per cent a year earlier, according to a summary cited in that reporting. The Detroit Free Press, reporting CDC data, said about 10 per cent of tests were positive in Arizona, California, Hawaii, Nevada and some US Pacific island territories. Katelyn Jetelina, an epidemiologist who consults for the CDC, wrote that the West was “clearly well on its way into the wave” and that flu would “slowly but surely move from the Pacific eastward in a sweeping motion,” according to the Detroit Free Press. In Michigan, by contrast, the CDC still classified flu-like activity as minimal in the week ending 17 October, although the trend was upward, the newspaper reported.
Epidemiologist Caitlin Rivers, director of the Center for Outbreak Response Innovation at Johns Hopkins University, wrote in an analysis on 25 October that children aged 1 to 4 and 5 to 17 had the highest share of emergency department visits for influenza, at between 2 and 3 per cent, while older adults, particularly those aged 75 and over, had the highest hospitalisation rates by far, at over 6 per 100,000 and climbing, according to the Detroit Free Press. Her figures come from a different cut of the surveillance data from the CDC’s FluSurv-NET rates above, so the two sets of numbers describe related but distinct measures. Together they reinforce the same practical point: children are showing up in emergency departments in larger shares, while older adults are the group most likely to need a hospital bed.
Behind the early wave is a virus that has changed in a specific, closely watched way. The circulating H1N1 viruses are A(H1N1)pdm09 viruses, the lineage that emerged in the 2009 pandemic and has caused seasonal epidemics globally since then, according to the CDC. The CDC said H1N1pdm09 viruses have historically changed less often than H3N2 viruses, but that the recently circulating H1N1 viruses, in a haemagglutinin subclade called D.3.1.1, are dividing into different groups showing different genetic changes. Of 317 H1N1 viruses genetically characterised by the CDC since 24 May 2026, 316, or 99.7 per cent, belonged to subclade D.3.1.1.
Researchers have focused on one change within that subclade: a mutation known as G155E in the virus’s haemagglutinin surface protein. Samuel Scarpino, executive director of the Institute for Experiential AI and a professor of public health and health sciences at Northeastern University, told Northeastern Global News that what the United States was seeing was “almost entirely H1N1, carrying a mutation that helps it evade some existing immunity.” He added: “This H1N1 variant appears to be behind the current surge and the early start.”
The Michigan Department of Health and Human Services, in its weekly Flu Focus report cited by the Detroit Free Press, said nearly all cases so far were influenza A(H1N1), and that most circulating H1N1 viruses carry the G155E mutation. “Studies suggest antibodies from past infections or vaccinations may not recognize it, especially in teens and young adults,” the Michigan report said, according to the newspaper. The mutation was detected in Japan as early as May 2026 and had been spreading gradually from August onward, according to Japan’s national infectious disease monitoring agency, as reported by Northeastern Global News. The surge in Japan led to school closures, and hospitals reported a jump in flu patients to roughly 11.35 per clinic for the week through 4 October, about a seven-fold increase from the previous year, according to the same reporting.
Scarpino offered a possible explanation for why younger people might be more affected by this change, rooted in the first flu strains a person encounters in childhood. “Our immune responses to flu are shaped by the first strains we encounter as children, and the 2009 H1N1 pandemic replaced the H1N1 strain that had been circulating,” he told Northeastern Global News. “Younger people’s first exposures were to that new strain, and this mutation hits a spot their immune systems tend to focus on.” That is a hypothesis about immune history, not a finding that younger people face the highest risk of severe illness: in the hospital data, older adults still have by far the highest rates.
Alex Greninger, head of the University of Washington’s Division of Infectious Disease Diagnostics, told CNN that as much as 98 per cent of the flu samples then arriving at his laboratory derived from H1N1, and that the laboratory was “basically seeing January levels of flu in the last week,” according to Gizmodo’s reporting of the CNN interview. Greninger raised the possibility of two flu seasons in one winter: an H1N1 wave peaking in 2026, followed by a more typical season in January, February or March driven by whatever strain follows. That remains speculation. No surveillance report has forecast a second peak, and the CDC has said it is too early to know which viruses will predominate.
The vaccine question is therefore two questions, not one: does this season’s vaccine recognise the circulating virus in the laboratory, and how well will it protect people in the real world? On the first question, the CDC’s laboratory work offers reassurance with limits. Of 88 H1N1 viruses antigenically characterised, 82, or 93.2 per cent, were well recognised by ferret antisera raised against the cell-grown A/Missouri/11/2025-like reference virus representing the H1N1 component of this season’s cell-, recombinant- and nucleic acid-based vaccines, according to the CDC. All 22 H3N2 viruses and all 30 B/Victoria viruses tested were also well recognised by antisera to their respective vaccine reference viruses.
The CDC was explicit about what those laboratory results do not prove. “It is too early to know what viruses may predominate or to say whether there might be implications on flu vaccine effectiveness this season,” the agency said, according to the report. Scarpino made the same distinction in plainer terms, telling Northeastern Global News that preliminary laboratory testing suggested the current vaccine should still recognise the strain, but that tests of human blood samples indicated that “some people,” like teenagers and young adults, may have less protection. He said public health officials would not have data on the vaccine’s effectiveness until midwinter, but added: “Still, early data shows the vaccine should provide meaningful protection, especially against severe illness, and it was updated against the H3N2 strain that may come later in the season. Now is the time to get vaccinated.”
The CDC recommends annual seasonal influenza vaccination for people aged 6 months and older, according to the report. For most people, vaccination should ideally be offered during September or October, the agency said, and vaccination during July and August is not recommended for most groups because immunity may wane over the course of the season. The Michigan health department put the same advice in direct terms, according to the Detroit Free Press: everyone aged 6 months and older is advised to get a flu shot, this year’s vaccine matches two of the three circulating strains very well, and over the past decade flu vaccines have cut flu hospitalisations and deaths by 30 to 60 per cent.
Last season is a useful reminder that a vaccine need not be highly effective at preventing every infection to prevent a large number of serious outcomes. Scarpino told Northeastern Global News that last year’s flu season was particularly severe, driven by an H3N2 variant that partially evaded existing immunity, including immunity from vaccination, and that the vaccine was about 30 to 40 per cent effective at preventing doctor visits and hospitalisations, lower than in recent years. Even so, during the 2022-23 season, when vaccine effectiveness was about 30 per cent, the CDC estimated that flu vaccination prevented more than 70,000 hospitalisations and roughly 3,700 deaths, Scarpino said. The lesson is not that effectiveness does not matter; it is that population-level benefit depends on both effectiveness and how many people are vaccinated, and that protection against severe illness is the outcome vaccination most reliably delivers.
Antiviral drugs remain a second line of defence, particularly for people at higher risk. The CDC said prescription flu antiviral drugs should be started as early as possible and are especially important for patients at higher risk of influenza complications. Laboratory testing since 24 May 2026 found reduced inhibition by oseltamivir, sold as Tamiflu, in eight of 329 H1N1 viruses tested, or 2.4 per cent, all carrying the amino acid substitutions NA-I223V and NA-S247N, according to the CDC. None of the viruses tested showed reduced inhibition by peramivir or zanamivir, and none showed decreased susceptibility to baloxavir. The small oseltamivir figure is a signal to monitor, not evidence that the drug has stopped working for most patients: more than 97 per cent of the H1N1 viruses tested did not show reduced inhibition. The CDC also noted that high levels of resistance to the adamantanes, amantadine and rimantadine, persist among influenza A viruses, and that those drugs are not recommended for treatment or prevention of influenza A infection.
For households, the practical sequence in the CDC’s guidance is straightforward, even if the virology is not. Vaccination is recommended now, in the September-to-October window the CDC identifies as ideal for most people. People at higher risk who develop flu symptoms should contact a clinician early about antivirals, because those drugs work best when started promptly. Anyone who is ill should follow local guidance on staying home and seeking care, and should seek urgent care for warning signs such as difficulty breathing, chest pain or confusion. Those are general public health recommendations, not a substitute for individual medical advice, and people with specific health conditions should discuss timing and vaccine choice with their own clinician or pharmacist.
Analysis: Why It Matters
1. A record for the calendar, not yet a crisis
The Week 41 comparison is best understood as a timing signal, not a severity forecast. The estimated rate of 1.5 to 2.0 hospitalisations per 100,000 people is small in absolute terms, and overall activity remains low by every other measure in the same report: outpatient illness is below baseline, emergency department visits are stable, and deaths attributed to influenza are flat. What makes the figure newsworthy is its position in the calendar. Hospitalisations at this level, this early, have not been seen in the surveillance network since 2010-11. That does not mean the season will be the worst since then, or that hospitals are under the kind of pressure they face in January. It means the season has started its climb from a higher base, and has more weeks in which to climb. Public health surveillance is designed to catch exactly this kind of early deviation, while there is still time for vaccination and preparation to change the slope.
2. Geography is the clue, and the warning
The west-first pattern matters for two reasons. First, it breaks the usual script. When a season begins in the south and moves north, eastern and northern states can watch the wave approach and prepare. When it begins on the Pacific coast, the direction of travel is less familiar, and the states that usually expect a later start may find the wave arriving sooner than their calendars suggest. Second, national averages hide local pressure. A national hospitalisation rate can look modest while individual metropolitan areas, which rose from eight to 25 at moderate activity in a single week, are already feeling strain in emergency departments and clinics. The useful question for the next few reports is therefore not only whether the national rate rises, but where it rises, and whether the moderate-activity areas broaden into a contiguous front or remain scattered hot spots that fade.
3. One mutation, two different questions
The G155E discussion often collapses two distinct scientific questions into one alarming claim. The first is whether the mutation helps the virus spread: by changing a spot on the haemagglutinin protein that antibodies focus on, it may allow the virus to infect people who carry some immunity from earlier H1N1 exposure, particularly younger people whose immune history is dominated by the post-2009 strain. The evidence for that is suggestive — the near-total dominance of H1N1, the early and western surge, and the laboratory and state-level reports linking the mutation to reduced antibody recognition — but researchers have not confirmed that the mutation alone explains the early start, and other factors, including behaviour, travel, waning immunity and the absence of a competing H3N2 wave, may also be at work. The second question is whether the mutation defeats this season’s vaccine. On that, the laboratory evidence so far points the other way: more than nine in ten H1N1 viruses tested were well recognised by vaccine antisera. Laboratory recognition is not the same as measured effectiveness in people, and effectiveness data will not arrive until midwinter, but the distinction matters. A virus can spread more easily among partially immune people while a vaccine still protects well against the severe outcomes that fill hospital beds.
4. The vaccine argument is about severity, not only infection
Much public debate about flu vaccination treats it as a promise not to catch flu. The surveillance record supports a narrower, stronger claim: vaccination reduces the risk of the outcomes that matter most — hospitalisation and death — even in seasons when it prevents only a minority of infections. Last season’s 30 to 40 per cent effectiveness against doctor visits and hospitalisations, in a severe H3N2 season, still translated into tens of thousands of hospitalisations prevented in an earlier season with similar effectiveness. That arithmetic is why public health officials urge vaccination in October even when a new variant is circulating: the benefit does not depend on the vaccine being a perfect shield, and it grows as more people in the groups most likely to be hospitalised — older adults, young children, pregnant people and those with chronic conditions — are protected before the peak. The counter-argument, that an imperfect match makes vaccination pointless, confuses the goal. The goal of a seasonal flu programme has never been zero infections; it is fewer severe infections, spread over a longer period, in a health system that can absorb them.
5. Do not let H5N1 confuse the H1N1 story
The single Washington dairy-worker H5N1 case in the same CDC report is a reminder of why surveillance systems test for more than one virus — and why precision in reporting matters. Avian influenza in cattle, and occasional human infections in people with close animal contact, are a distinct and serious monitoring task, with its own precautions for farm workers and its own criteria for concern, above all sustained human-to-human transmission, which the CDC says has not been identified in the United States. Treating that case as part of the seasonal flu wave would overstate the bird flu risk and understate the seasonal one, by implying that the hospitalisations now rising are somehow avian in origin. They are not: the hospitalised patients in FluSurv-NET overwhelmingly had seasonal H1N1. Conversely, dismissing the H5N1 case because it is only one infection would miss the point of the system that found it. A surveillance network that can distinguish a seasonal virus, a low-level H3N2 presence and a single occupational H5N1 infection in the same week is doing exactly what it is built to do, and the public value of that distinction will only grow if either virus changes.
What to Watch Next
- The Week 42 FluView report: the CDC’s next weekly update, covering the week ending 24 October, will show whether hospital admissions kept rising nationally, whether the estimated FluSurv-NET rate held above its Week 41 range, and whether the Southeast, which had the highest hospital admission rate in Week 41, continued to lead or the West reasserted itself.
- Whether H3N2 or influenza B rises later: H1N1 dominates now, but H3N2 circulated last season and was present at low levels in the cumulative subtyping data. A second strain rising in January or February, as researchers have hypothesised, would change the shape of the season and test the vaccine component updated against last season’s H3N2 variant.
- Vaccine effectiveness estimates in midwinter: laboratory recognition is encouraging, but real-world effectiveness, and any age-specific differences for teenagers and young adults, will not be known until the CDC and its partners publish interim estimates. Those figures, not the G155E label alone, will settle how well this season’s vaccine performed.
- Hospital capacity in the regions moving first: national rates remain low, but local emergency department and admission trends in the West and Southeast, and in the metropolitan areas that moved to moderate activity, will show whether early pressure stays local or becomes a broader strain on care as respiratory viruses co-circulate.
- Follow-up on the Washington H5N1 case: any further human cases linked to dairy cattle, any evidence of onward transmission, and any change in CDC or state guidance for exposed workers would be a separate and significant development, distinct from the seasonal H1N1 trend.
Sources
- CDC, Weekly US Influenza Surveillance Report: Key Updates for Week 41, ending October 17, 2026
- Northeastern Global News, What to Know About the Mutated Flu Strain and the Vaccine
- Detroit Free Press, Flu wave hits U.S. early. What’s happening in Michigan?
- Cleaning & Maintenance Management, Early Flu Season Starts on the West Coast (reporting Reuters)
- Becker’s Hospital Review, Flu hospitalization rate hits highest mid-October level since 2010: 5 notes

About the Author — Abdul Mannan
Related Articles

Ebola Nurse Killed in Congo Attack as WHO Warns Violence Is Now Threatening the Response
A nurse responding to an Ebola alert in Bafwasende, in eastern Congo, has been killed by protesters and…

Kenya Records Second Ebola Death as Regional Outbreak Spreads to Four Countries
Kenya's health ministry has confirmed a second Ebola death, a 65-year-old close relative of the country's first patient,…
Deadliest on Record: Europe’s Summer Heat Killed an Estimated 50,000 People, Study Finds
A new study in Nature Health estimates 50,391 heat-related deaths across 854 European cities this summer — the…