
FDA Approves Sunharbo, the First Factor XIa Blood Thinner, to Cut the Risk of Repeat Strokes

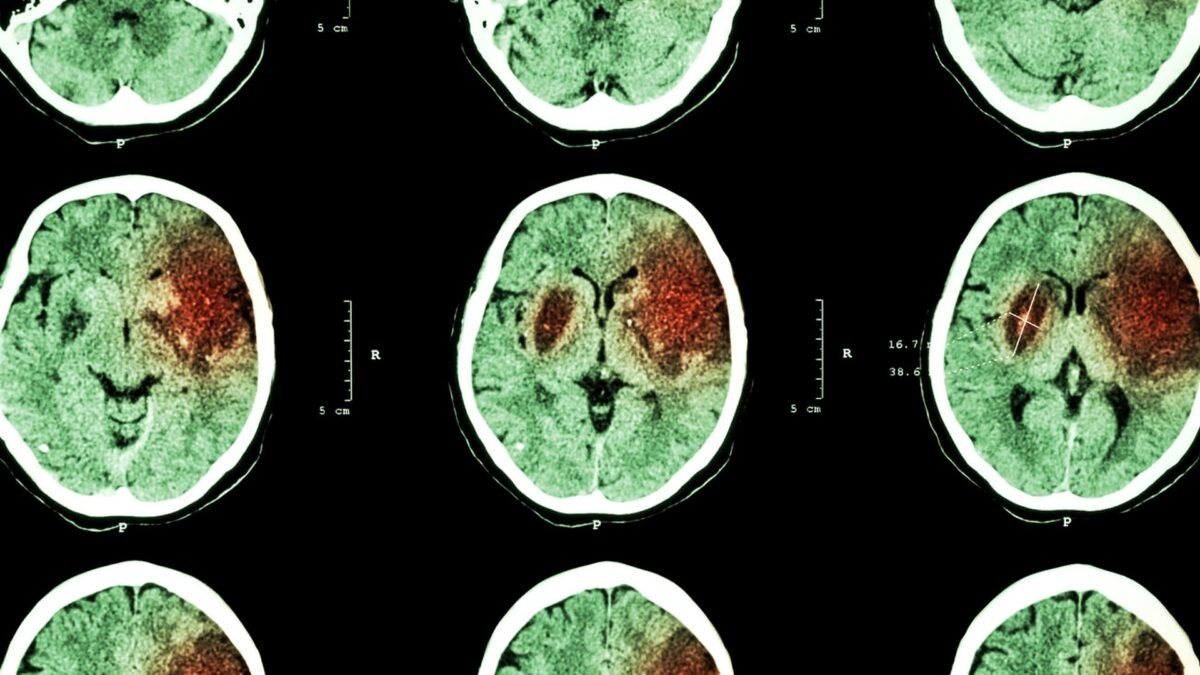
The United States Food and Drug Administration has approved a new blood thinner that works in a way no approved medicine has before, clearing the way for the first drug designed to block the clotting protein Factor XIa and cut the risk of a second stroke. The decision, announced on Monday, 9 November 2026, gives stroke survivors and their doctors a new option in a part of medicine where the standard treatments have barely changed in more than a decade.
The drug is called Sunharbo, known by its chemical name asundexian, and it is made by the German pharmaceutical company Bayer. According to the FDA, the once-daily 50 mg tablet is approved for adults who have recently had a mild-to-moderate ischemic stroke that was not caused by a clot travelling from the heart, or who have had a high-risk transient ischemic attack, often called a mini-stroke. It must be taken together with standard antiplatelet therapy, the blood-thinning tablets such as aspirin or clopidogrel that stroke patients already receive.
According to Reuters, which first reported the approval, Sunharbo is the first approved treatment that prevents harmful blood clots by blocking Factor XIa. The widely used blood thinners of today, including Eliquis and Xarelto, work by blocking a different protein in the clotting chain, Factor Xa. The FDA listed Sunharbo among its novel drug approvals for 2026, and the agency had previously granted the medicine Fast Track and Priority Review designations, which speed up the review of drugs that may fill an unmet medical need.
The approval rests on a single large trial, and the numbers behind it are striking. In the phase 3 OCEANIC-STROKE study, patients who took asundexian alongside antiplatelet therapy were 26 percent less likely to suffer another ischemic stroke than patients who took a placebo with the same background treatment. The result was published in the New England Journal of Medicine in April 2026, and the FDA cited the trial as the basis for its decision.
What Sunharbo Is and How It Works
To understand why this approval matters, it helps to understand what happens inside the body when a stroke strikes. An ischemic stroke, which accounts for about 87 percent of all strokes, happens when a blood clot blocks an artery carrying blood to the brain. Starved of oxygen, brain cells begin to die within minutes. The danger does not end when the first stroke is treated. A patient who has had one stroke faces a sharply higher risk of having another, and the weeks and months after the first event are the most dangerous period of all.
Doctors have long tried to lower that risk with antiplatelet drugs, which make platelets less likely to clump together, and with anticoagulants, which interfere with the chain of chemical reactions that forms a clot. The most powerful anticoagulants in common use, the Factor Xa inhibitors, are effective, but they carry a price: by blocking a protein that the body needs for normal clotting, they raise the risk of serious bleeding. That trade-off has limited how aggressively doctors can treat many patients.
Factor XIa sits further along the clotting chain, and it plays a much larger role in the formation of harmful clots than it does in the everyday clotting that stops a cut from bleeding. The idea behind targeting it, which researchers have pursued for more than a decade, is that blocking Factor XIa might prevent the dangerous clots while leaving the body’s normal ability to stop bleeding largely intact. According to Bayer, asundexian is a selective, once-daily oral inhibitor of Factor XIa, designed to reduce the formation of pathological clots while largely preserving normal haemostasis.
Until now, that idea had never produced an approved medicine. Sunharbo is the first Factor XIa inhibitor to reach patients anywhere in the world through a major regulator, and the first new mechanism for oral anticoagulation to win approval in more than a decade.
The Trial Behind the Approval
The OCEANIC-STROKE trial was one of the largest stroke-prevention studies ever run. According to the FDA and Bayer, it enrolled 12,327 adults at 702 centres in 37 countries. Participants were randomly assigned within 72 hours of a non-cardioembolic ischemic stroke, with a stroke severity score of 15 or less on the National Institutes of Health Stroke Scale, or a high-risk transient ischemic attack. Half received 50 mg of asundexian once a day, and half received an identical placebo, with both groups continuing their planned single or dual antiplatelet therapy.
Over a median follow-up of 14.2 months, recurrent ischemic stroke occurred in 6.2 percent of the patients taking asundexian, compared with 8.4 percent of those taking placebo. That is 384 of 6,162 patients on the drug against 518 of 6,165 on placebo. The relative reduction was 26 percent, with a hazard ratio of 0.74 and a 95 percent confidence interval of 0.65 to 0.84, a result that was highly statistically significant, with a P value below 0.0001.
According to Reuters, the study also showed that the drug reduced both the frequency and the severity of recurrent ischemic strokes. That second point matters, because a second stroke is often more disabling than the first, and a treatment that makes repeat strokes milder as well as rarer would change the outlook for survivors in a meaningful way.
The safety results were the part of the trial that many specialists had been waiting for, because the whole case for Factor XIa inhibition rests on the promise of preventing clots without causing the bleeding that limits older blood thinners. Major bleeding, measured by the International Society on Thrombosis and Haemostasis definition, occurred in 1.9 percent of patients on asundexian and 1.7 percent on placebo, a hazard ratio of 1.10 with a confidence interval of 0.85 to 1.44, which means the difference was not statistically significant. In plain terms, adding the drug to antiplatelet therapy did not produce a meaningful increase in major bleeding in the trial population.
There was one cautionary note in the data. A secondary outcome measured at 90 days, an earlier look at the same question, missed statistical significance, with a hazard ratio of 0.84 and a confidence interval of 0.69 to 1.02. That does not undermine the main result, which was measured over the full follow-up period, but it is a reminder that the benefit builds over time and that the drug is a long-term preventive treatment rather than an emergency therapy.
Safety, Limits and Who It Is Not For
The approval is deliberately narrow, and the limits are as important as the headline. Sunharbo is approved only for adults after a recent mild-to-moderate non-cardioembolic ischemic stroke or a high-risk transient ischemic attack. Non-cardioembolic means the clot did not come from the heart, and that distinction decides who can receive the drug.
According to the FDA, Sunharbo is not approved to prevent strokes in people with atrial fibrillation, the irregular heartbeat that sends clots from the heart to the brain. That is the largest single market for blood thinners, and the exclusion has a history. Bayer halted a separate trial, OCEANIC-AF, after an interim analysis showed that asundexian was less effective than apixaban, sold as Eliquis, at preventing strokes in people with atrial fibrillation. Patients with that condition will continue to rely on the established Factor Xa inhibitors and other existing treatments.
The FDA also states that the drug is not recommended for patients with moderate or severe liver impairment, and that it should not be taken together with medicines that combine P-glycoprotein and strong CYP3A4 induction, because those medicines can reduce its effectiveness. As with all anticoagulants, bleeding remains a risk that doctors must weigh for each patient, and the drug must be taken alongside antiplatelet therapy rather than instead of it.
These limits are not a footnote. They define the population in which the drug was actually tested, and prescribing outside that population would mean using the medicine without evidence. The approval covers only the group studied in OCEANIC-STROKE, and doctors are expected to stay inside that boundary.
A Long Road From Setback to Approval
Sunharbo’s journey to approval was neither short nor smooth, and the history matters because it explains why specialists have watched this drug so closely. The phase 2b PACIFIC-STROKE trial, which came before the large phase 3 study, did not meet its primary endpoint, a combined measure of covert brain infarction and ischemic stroke. But it did show a signal that the 50 mg dose reduced symptomatic strokes, particularly among patients whose strokes were caused by atherosclerosis, the narrowing of arteries, without increasing major or clinically relevant bleeding. That signal was enough for Bayer to press ahead with the much larger OCEANIC-STROKE trial.
The company announced the positive results of OCEANIC-STROKE on 23 November 2025, and the full findings were published in the New England Journal of Medicine in April 2026, in a paper led by M. Sharma and colleagues. The FDA accepted the new drug application under priority review in May 2026, and the approval followed less than six months later.
China’s drug regulator approved the medicine on 26 October 2026, making the United States the second major market to clear it. According to Bayer, the drug is currently under review by the European Medicines Agency and by Japan’s Ministry of Health, Labour and Welfare. The company said it expects Sunharbo to begin shipping in mid-to-late November, and to become available for hospitals and pharmacies to order across the United States shortly afterwards. Neither the FDA nor Bayer announced a price on the day of approval.
The Scale of the Problem
The reason a new stroke drug matters so much is the sheer scale of the disease it targets. According to the World Health Organization, about 15 million people around the world suffer a stroke every year. Of those, around 5 million die and another 5 million are left permanently disabled. The most recent Global Burden of Disease estimates, summarised in a 2026 fact sheet, put the toll at 13.2 million new strokes in 2023, with 104.8 million people living with the consequences of a stroke and 6.8 million stroke-related deaths, accounting for 156.5 million disability-adjusted life years lost. Stroke was the second leading cause of death worldwide and the third leading cause of death and disability combined.
More than 80 percent of stroke deaths and disability occur in low- and middle-income countries, and ischaemic stroke accounts for almost two-thirds of new cases. Overall, 83 percent of the global stroke burden is attributable to modifiable risk factors, with high blood pressure the leading contributor. The figures describe a disease that is both enormous and, to a large degree, preventable, which is why every improvement in treatment carries such weight.
In the United States, Bayer estimates that about 795,000 people have a stroke each year, according to Reuters, and stroke remains a leading cause of death in the country. According to the US Centers for Disease Control and Prevention, nearly 800,000 Americans have a stroke each year, and about 185,000 of those are repeat strokes in people who have already had one. The American Stroke Association notes that about one in four stroke survivors will have another stroke within five years. Behind each of those numbers is a person who survived a first stroke and then spent the following months and years living with the fear of a second.
Sebastian Guth, president of Bayer’s US operations, told Reuters that the company believes it is bringing a practice-changing innovation to the market. “There have not been any changes in the recurrence rates of stroke over the past 20 years, so there’s a genuine and very significant excitement” for the drug, he said. That claim goes to the heart of why this approval has drawn attention: for two decades, the risk of a second stroke has barely moved, despite better emergency care and wider use of existing preventive drugs.
What Happens Next
The immediate question is how quickly Sunharbo reaches patients. Bayer has said shipments will begin in mid-to-late November, which means the drug should be available in American hospitals and pharmacies before the end of the year. The bigger questions, price and insurance coverage, remain unanswered. The company has previously described the drug as having blockbuster potential, a term the industry uses for medicines expected to generate at least 1 billion dollars in annual sales, and Reuters reported that Bayer is counting on it to help offset falling revenue from older blockbuster medicines such as Xarelto, which has faced competition from cheaper generic versions after losing patent protection.
Regulators in Europe and Japan are still reviewing the drug, and their decisions will shape how widely it is used. A positive decision from the European Medicines Agency would open the door to the world’s second-largest medicines market, while a rejection or a demand for more data would slow the drug’s global rollout considerably.
Competition is also coming. According to Reuters, other drugs in development that could eventually compete with Sunharbo include abelacimab from Novartis and milvexian, a joint effort by Bristol Myers Squibb and Johnson and Johnson. Both target the same Factor XIa pathway, but neither has yet reported late-stage stroke-prevention data. If either succeeds, the new class could grow quickly. If either fails, Sunharbo may stand alone for years, carrying the weight of proving that the Factor XIa idea works in routine practice and not only in a carefully controlled trial.
Analysis: Why It Matters
The approval of Sunharbo matters for three separate reasons, and they are worth keeping apart. The first is the most obvious: stroke survivors now have a new medicine that has been shown, in a large and rigorous trial, to reduce the chance of a second stroke by about a quarter. A 26 percent relative reduction sounds abstract until it is translated into human terms. In the trial, 2.2 fewer patients out of every 100 had another stroke while taking the drug. Across the hundreds of thousands of people who have a stroke each year in the United States alone, that difference would mean tens of thousands of second strokes prevented, each one a hospital admission, a rehabilitation, and often a permanent disability avoided.
The second reason is the safety result, which is arguably the more important of the two. Every blood thinner ever made has forced doctors to choose between preventing clots and causing bleeding. The trial showed that asundexian, added to antiplatelet therapy, cut repeat strokes without a statistically significant increase in major bleeding. If that finding holds up in everyday practice, outside the carefully selected population of a clinical trial, it would mean the old trade-off can be softened. That is the promise that has driven more than a decade of research into Factor XIa, and it is the reason specialists have described the drug as a genuine advance rather than simply another option on the shelf.
The third reason is what the approval says about how drug development works when it works well. This programme nearly died more than once. The phase 2b trial missed its main endpoint. The atrial fibrillation trial was stopped for lack of effectiveness. A less determined company might have abandoned the drug entirely. Instead, Bayer read the signals in the data, narrowed the focus to the patients most likely to benefit, and ran one of the largest stroke trials ever conducted. The result is a medicine approved for a precisely defined group, with honest limits, on the basis of strong evidence. That is how the system is supposed to work, and it does not always do so.
At the same time, the limits of this approval deserve to be stated plainly, because enthusiasm without caution would do patients no good. The approval rests on a single phase 3 trial, funded by the manufacturer, with a median follow-up of 14.2 months. That is a substantial body of evidence, but it is not the same as decades of experience with older drugs. Real-world use will involve older patients, sicker patients, and patients taking many other medicines, none of whom were fully represented in the trial. Bleeding events that are rare enough to be invisible in a trial of 12,000 people can become visible when a drug is taken by hundreds of thousands.
The exclusion of atrial fibrillation is the largest gap. The irregular heartbeat is one of the commonest causes of stroke, and the patients who need anticoagulation most urgently are precisely the ones this drug cannot yet help. The failure of OCEANIC-AF is a reminder that the Factor XIa story is not a simple triumph. The mechanism that works after an artery-driven stroke did not work when the clot came from the heart, and nobody yet fully understands why. Until that question is answered, Sunharbo will be a medicine for some stroke survivors, not all of them.
Price will decide how much of the benefit actually reaches patients. Bayer has not announced what Sunharbo will cost, and American patients already face high out-of-pocket costs for newer medicines. A drug that prevents second strokes is valuable, but only if the people at risk can afford to take it every day for years. Insurers will weigh the trial result against the cost, and their coverage decisions in the coming months will matter as much as the FDA’s approval in determining who benefits. In lower-income countries, where more than 80 percent of the world’s stroke deaths occur, the question is sharper still: a medicine priced for wealthy health systems will not reach the places where the burden is heaviest.
There is also a wider lesson here for medicine. The Factor XIa idea was built on a simple observation about human biology: some people born with low levels of Factor XI rarely suffer strokes and rarely bleed badly either. Turning that observation into a drug took more than a decade, several failed trials, and a very large bet by one company. The approval vindicates the slow, unglamorous work of following a biological clue through failure after failure. It is a reminder that the most important advances in medicine often arrive not as sudden breakthroughs but as the end of a long road that many people had written off.
For patients and families, the practical advice is unchanged and straightforward. Sunharbo is a prescription medicine for a specific group of people, and it is not a substitute for the measures that prevent strokes in the first place: controlling blood pressure, stopping smoking, managing diabetes and cholesterol, and taking prescribed medicines as directed. Anyone who has had a stroke or a mini-stroke should discuss with their doctor whether the new treatment is appropriate for them, and should not change or stop any existing treatment without medical advice.
What to Watch Next
Several things will show, over the coming year, whether Sunharbo lives up to its promise. The first is the European Medicines Agency’s decision, which will determine whether the drug becomes a global treatment or remains confined to the United States and China. The second is the price, and the speed with which insurers agree to cover it. The third is the real-world safety data that will accumulate as the drug moves from a trial population of 12,327 carefully chosen patients into everyday use, where the patients are older, sicker, and more complicated.
Doctors will also watch for results from the rival Factor XIa drugs, abelacimab and milvexian, which could either confirm the class as a whole or raise new questions about it. And researchers will continue to ask the question that OCEANIC-AF left unanswered: why does blocking Factor XIa work after one kind of stroke and not another? The answer to that question could shape the next generation of blood thinners.
For now, though, the fact that matters is simple. After twenty years in which the risk of a second stroke barely moved, a new medicine has been approved that reduces that risk by a quarter, without meaningfully increasing major bleeding. For the millions of people who live with the fear of a second stroke, that is not a small thing.
Sources
- US Food and Drug Administration: FDA approves first Factor XIa inhibitor to help prevent stroke in certain adults at high risk, 9 November 2026
- Reuters: US FDA approves Bayer’s blood thinner to prevent repeat strokes, 9 November 2026
- Bayer / Business Wire: Bayer’s SUNHARBO (asundexian), the first and only Factor XIa inhibitor, approved by the US FDA, 9 November 2026
- Sharma M, Dong Q, Hirano T, et al. Asundexian for Secondary Stroke Prevention. New England Journal of Medicine 2026;394(15):1467–1479
- US Food and Drug Administration: Novel Drug Approvals for 2026

About the Author — Abdul Mannan
Related Articles

Bangladesh Measles Death Toll Reaches 1,284 as Outbreak Becomes the Country’s Deadliest in Decades
Two more children have died in Bangladesh's measles outbreak, taking the death toll to 1,284 as the country…

Johnson & Johnson’s Once-Daily Pill Eases Psoriatic Arthritis in Late-Stage Trial, Offering Hope of an Injection-Free Option
Johnson & Johnson says its once-daily pill ICOTYDE met its main goal in a 552-patient Phase 3 trial,…
US Measles Cases Pass 5,000 for First Time Since 1991 as Infant Death in Wisconsin Brings Toll to Eight
Measles cases in the United States have passed 5,000 in a single year for the first time since…